
PectusExcavatum AI Coach Open the app

Guide

Pectus carinatum (pigeon chest)

In pectus carinatum the breastbone sticks out instead of sinking in. It usually shows up in the early teens, and unlike pectus excavatum it often responds well to a brace.

Updated November 22, 2026 · 7-minute read

What it is

Pectus carinatum, also called pigeon chest, is a forward protrusion of the breastbone and the rib cartilages beside it. It is the second most common chest wall deformity after pectus excavatum.

How common it is

Estimates range from about 1 in 2,500 to 1 in 1,000 people. In a school screening in Brazil it was found in 0.7% of children aged 11–14, about half as often as pectus excavatum. It mostly affects boys: around 4 to 1, and close to 9 boys out of 10 in bracing studies.

When it appears

It is often mild or barely visible in childhood and becomes prominent during the growth spurt. In a surgical series almost half of patients were first noticed after age 11.

The types

  • Chondrogladiolar, the common form (up to 95% of cases): the middle and lower part of the sternum sticks out, like the keel of a boat.
  • Chondromanubrial (also called Currarino-Silverman or “pouter pigeon”): rare. The upper part of the sternum sticks out and the lower part is sunken. It is more often associated with congenital heart defects and is treated differently.
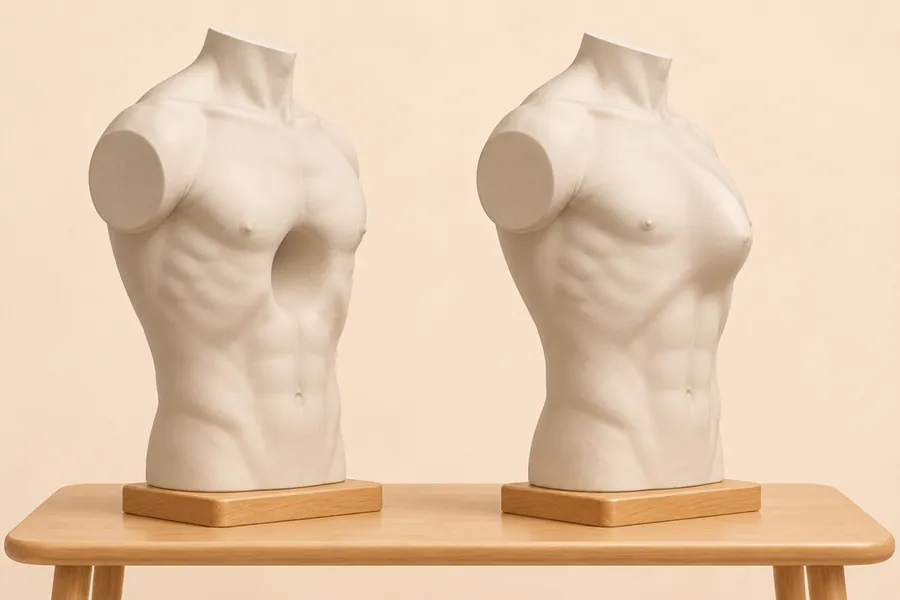
  • Symmetric, asymmetric or mixed: in a series of 152 patients, 89 were symmetric, 49 asymmetric and 14 mixed, with one side protruding and the other sunken. Mixed forms are covered in excavatum vs carinatum.

Causes and related conditions

The cause is unknown and may be similar to that of pectus excavatum. It runs in families: about a quarter to a third of patients have an affected relative. It can go with scoliosis (15% in one series), and less often with Marfan or Noonan syndrome, homocystinuria, mitral valve prolapse or Poland syndrome. Signs of these conditions are worth discussing with a doctor.

Symptoms

For most people it is mainly a matter of appearance. Some have tenderness or pain over the protrusion, for example when lying on their front. Physical symptoms are generally fewer than with pectus excavatum, but the effect on how people feel can be large: in one study, patients with carinatum were even less satisfied with their appearance than those with excavatum.

How it’s assessed

The diagnosis is clinical: a doctor looks at the shape and checks how flexible the chest is. Bracing centers measure the pressure needed to push the sternum back into place, which helps decide whether a brace can work. Imaging is not always needed; when it is done, a modified Haller index can describe severity.

The brace

For a flexible chest, dynamic compression bracing is the first choice, and the 2024 UK guideline rates it highly effective and safe. A custom brace presses on the protruding sternum and, worn for months, lets the chest wall remodel.

  • How long: in the Argentinian system that introduced pressure measurement, patients wore it on average 7 hours a day for 7 months; in a Dutch series of 286 patients, treatment lasted 14 months on average.
  • Results: among patients who completed treatment, 88% had a good or excellent result in the first series. In a stricter prospective study, success was 56%, with lower chances in older and asymmetric patients.
  • Problems: in a review of 1,185 patients, discomfort in 12%, skin lesions in 5%, recurrence in about 3%. Many stop early: 6% dropped out and 21% were lost to follow-up.
  • What makes the difference: wearing it as prescribed. Taller patients and stiffer chests need longer.

Surgery

Surgery is considered when the chest is rigid, bracing has failed or the shape is complex. The open modified Ravitch procedure reshapes the cartilages and the sternum: in a series of 260 patients, 97% had a very good or excellent result. The minimally invasive Abramson technique presses the sternum down with a bar outside the ribs: in a review of 396 patients, 91% were satisfied after bar removal, with 3% recurrence but complications in about a quarter. For complex or mixed forms, some centers use a combined “sandwich” technique.

Exercise

There is no evidence that exercise corrects pectus carinatum. Strength training can still help how the chest looks and how you hold yourself, and it’s good for you, but it doesn’t replace a brace. The exercises in the Pectus app are designed for pectus excavatum.

Frequently asked questions

Is pigeon chest dangerous?

Usually not: it is mainly a matter of appearance, sometimes with local tenderness. It is worth checking for related conditions such as scoliosis or Marfan syndrome.

Can a brace fix pectus carinatum?

Often, if the chest is still flexible: dynamic compression bracing is the first-line treatment, with good results in most patients who wear it as prescribed.

How long do you wear a pectus carinatum brace?

Typically several months to over a year: 7 months on average in one series, 14 in another. Taller patients and stiffer chests need longer.

Can exercise fix pigeon chest?

No study shows it. Training can improve posture and how the chest looks, but it doesn’t reshape the sternum.

Does pectus carinatum need surgery?

Rarely as a first step. Surgery is for rigid chests, complex shapes or when bracing hasn’t worked.

Sources

  1. Dunning J, Burdett C, Child A, et al. The pectus care guidelines: best practice consensus guidelines from the joint specialist societies SCTS/MF/CWIG/BOA/BAPS for the treatment of patients with pectus abnormalities. Eur J Cardiothorac Surg 2024;66(1):ezae166.
  2. Janssen N, Coorens NA, Franssen AJPM, et al. Pectus excavatum and carinatum: a narrative review of epidemiology, etiopathogenesis, clinical features, and classification. J Thorac Dis 2024;16(2):1687–1701.
  3. Westphal FL, Lima LC, Lima Neto JC, et al. Prevalence of pectus carinatum and pectus excavatum in students in the city of Manaus, Brazil. J Bras Pneumol 2009;35(3):221–6.
  4. Shamberger RC, Welch KJ. Surgical correction of pectus carinatum. J Pediatr Surg 1987;22(1):48–53.
  5. Cleveland Clinic. Pectus carinatum (updated August 2023). clevelandclinic.org
  6. Robicsek F, Watts LT. Pectus carinatum. Thorac Surg Clin 2010;20(4):563–74.
  7. Gritsiuta AI, Bracken A, Beebe K, Pechetov AA. Currarino-Silverman syndrome: diagnosis and treatment of rare chest wall deformity, a case series. J Thorac Dis 2021;13(5):2968–78.
  8. Steinmann C, Krille S, Mueller A, et al. Pectus excavatum and pectus carinatum patients suffer from lower quality of life and impaired body image: a control group comparison of psychological characteristics prior to surgical correction. Eur J Cardiothorac Surg 2011;40(5):1138–45.
  9. Martinez-Ferro M, Fraire C, Bernard S. Dynamic compression system for the correction of pectus carinatum. Semin Pediatr Surg 2008;17(3):194–200.
  10. de Beer SA, Gritter M, de Jong JR, van Heurn ELW. The dynamic compression brace for pectus carinatum: intermediate results in 286 patients. Ann Thorac Surg 2017;103(6):1742–9.
  11. de Beer S, Volcklandt S, de Jong J, Oomen M, Zwaveling S, van Heurn E. Dynamic compression therapy for pectus carinatum in children and adolescents: factors for success. J Pediatr Surg 2023;58(8):1440–5.
  12. de Beer SA, Blom YE, Lopez M, de Jong JR. Measured dynamic compression for pectus carinatum: a systematic review. Semin Pediatr Surg 2018;27(3):175–82.
  13. Emil S, Sévigny M, Montpetit K, et al. Success and duration of dynamic bracing for pectus carinatum: a four-year prospective study. J Pediatr Surg 2017;52(1):124–9.
  14. Cohee AS, Lin JR, Frantz FW, Kelly RE Jr. Staged management of pectus carinatum. J Pediatr Surg 2013;48(2):315–20.
  15. Hunt I, Patel AJ. Effectiveness of compressive external bracing in patients with flexible pectus carinatum deformity: a review. Thorac Cardiovasc Surg 2020;68(1):72–9.
  16. Fonkalsrud EW. Surgical correction of pectus carinatum: lessons learned from 260 patients. J Pediatr Surg 2008;43(7):1235–43.
  17. Geraedts TCM, Daemen JHT, Vissers YLJ, et al. Minimally invasive repair of pectus carinatum by the Abramson method: a systematic review. J Pediatr Surg 2022;57(10):325–32.
  18. Park HJ, Kim KS. The sandwich technique for repair of pectus carinatum and excavatum/carinatum complex. Ann Cardiothorac Surg 2016;5(5):434–9.